
In this article you read why your gut behaves so changeably, what you can measure yourself and when to see your GP. That is important, because it tells you what you can follow yourself. One week you go three times a day, the next week almost not at all. Your stomach hurts after eating, or for no reason, and you never know what kind of day it will be. Gut complaints are among the most common complaints there are. The BioProfile gut scan measures how much trouble you have from those complaints, and gives you an indication of where you stand today in this area, as the first of the 11 health areas that the full scan assesses. This is not a diagnosis. It is insight, to see where you stand today. And to help you make better choices in your food and lifestyle. What this scan does not do: point out a cause or make a diagnosis. Only a doctor can do that.

Verified by Carlos Mendoza Montano
Doctorate in nutritional biochemistry from the University of Arizona
Checked on 1 October 2026
In short
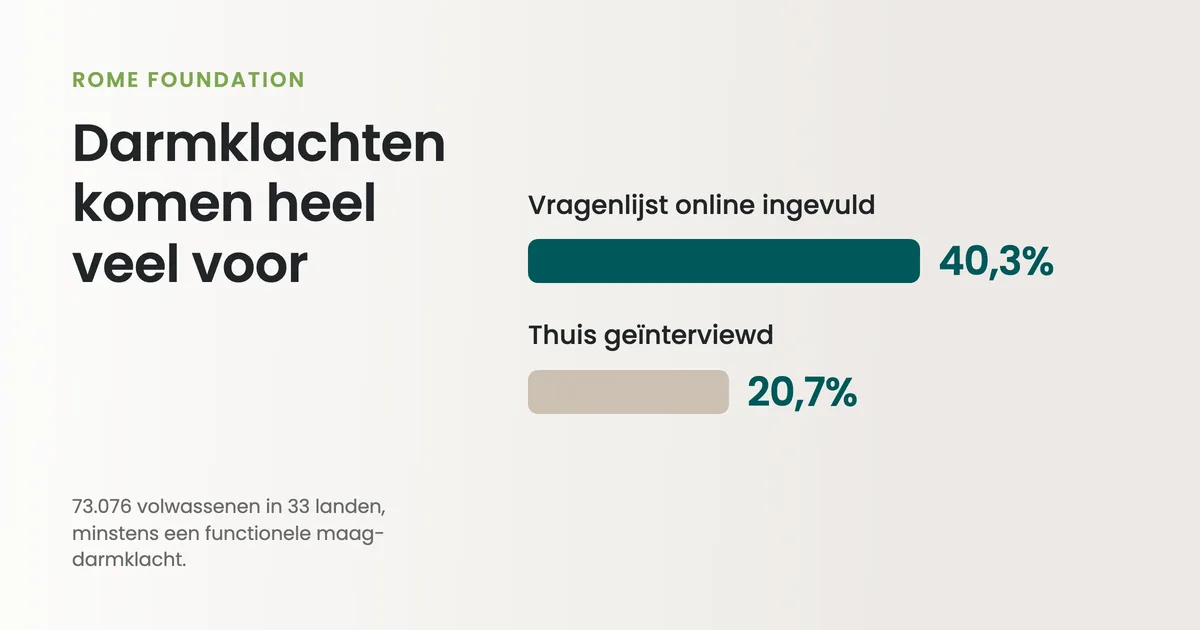
- More than 40 per cent of the people who filled in a worldwide questionnaire online met the criteria for at least one functional stomach or bowel complaint.1
- Blood in your stool, your weight going down without knowing how, or getting bowel complaints for the first time when you are 50 or older: those are three reasons for the GP and not for a score.2
- A gut scan gives you an indication of where you stand today with your symptom load over the past few weeks, and a starting value. It is not a diagnosis, and this scan does not point to a cause.
Contents
How common gut complaints are
The Rome Foundation asked 73,076 adults in 33 countries about their gut. Of the people who filled in the questionnaire online, 40.3 per cent met the criteria for at least one functional gastrointestinal complaint; among the people who were interviewed at home it was 20.7 per cent. Women more often than men. What you call it depends on which criteria you use: with the newest criteria 4.1 per cent had irritable bowel syndrome, with the previous ones 10.1 per cent.1 In the Netherlands about one in 25 people has it.2
The complaints rarely come alone. In the same worldwide study almost 18 per cent had a bloated stomach at least once a week, and of the people with weekly abdominal pain more than six in ten had that too.3
Why your gut does what it wants
In irritable bowel syndrome the gut is not inflamed and not damaged; it works and responds differently than in people without complaints.2 What that “differently” looks like has been measured. As early as 1975 it turned out that people with chronic gas complaints did not have more gas in their gut than people without complaints, on average 176 against 199 millilitres, but that in those who got pain the gas took longer to pass and that the same amount hurt more.4 The researchers concluded that complaints of a bloated stomach, pain and gas can come from a disturbed movement of the gut, together with an abnormal pain response to a stretched gut, and not from more gas.4
The criterion doctors use to recognise irritable bowel syndrome fits with that: abdominal pain that came back on average at least one day a week over the past three months and is linked to at least two of these three: passing stool, a change in how often you go and a change in how your stool looks; the complaints started at least six months earlier.5 For some people food weighs heavily. In a controlled study thirty people with irritable bowel syndrome ate a diet low in fermentable carbohydrates for three weeks and a normal Australian diet for three weeks. Their complaint score was 22.8 on the first diet and 44.9 on the second, on a scale of 100; in healthy people the diet did nothing.6
What a gut scan measures
The gut scan asks six questions about the past few weeks: the form of your stools, belly pain or discomfort, a bloated feeling, how regularly you go, reflux or heartburn, and complaints after certain foods. Each question is given points, the points are added up and converted into a gut score from 0 to 100, with the reading band it falls into. Higher is better.
The questions are modelled on two validated complaint scales. The Bristol Stool Form Scale reads the shape of your stool as a signal of how fast your gut works: in 66 volunteers whose transit time was measured, the shape was the best predictor, better than how often they went, and when transit changed, the shape changed with it.7 The Gastrointestinal Symptom Rating Scale assesses stomach and gut complaints with fifteen questions, and that set-up is our model.8 Our own questions are written by us, not a copy, so the score is not a validated clinical score. What you get is a structured picture of your complaint burden and a baseline.
What a gut scan does not measure
A questionnaire reads the load you describe. It cannot see whether this is irritable bowel syndrome, an intolerance, coeliac disease or something that clears up on its own. That needs a doctor, and sometimes blood or stool tests. So a gut scan does not make a diagnosis. A low score means that looking further makes sense, and nothing more.
The GP asks questions and examines your belly; tests in hospital are usually not needed, and blood or stool tests follow when something else is suspected, such as coeliac disease. Three things are a reason to make an appointment: blood in or mixed through your stool, your weight going down without knowing why that happens, and getting bowel complaints for the first time when you are 50 years or older.2
What you do with your score
Gut complaints change from day to day, and that is exactly why you remember them badly: a good week wipes out a bad one. A score from today is your baseline. Repeat the scan in a few weeks, over the same questions, and you have two numbers instead of a feeling.
If you want to do something in those weeks, keep track of two things: the shape of your stools, because that gives an indirect clue to how fast your bowel works,7 and the days with pain, together with what you ate that day. That is the information a GP or dietitian can work with, and that a questionnaire does not collect for you.
Measure where you start
Six questions about the past few weeks, about three minutes, and your gut score is in your dashboard. What the gut scan measures and what it is based on is set out on the scan page.
Free, about 3 minutes. An analysis of your answers, never a diagnosis. All health scans
Frequently asked questions
What are the symptoms of gut problems?
Abdominal pain or cramps that move from place to place, a bloated stomach, constipation, diarrhoea, a lot of wind and mucus in your stool. The complaints change from day to day and differ from person to person.2
How do I know if I have irritable bowel syndrome?
The criteria: abdominal pain that came back on average at least one day a week over the past three months and is linked to at least two of these three: passing stool, a change in how often you go and a change in how your stool looks; the complaints started at least six months earlier.5 Whether that is the case for you is something the GP assesses with questions and an examination of your stomach; tests in hospital are usually not needed.2 A questionnaire cannot establish it.
Which gut complaints are a reason to see your GP?
Blood in or mixed through your stool, your weight going down without knowing why that happens, and getting bowel complaints for the first time when you are 50 years or older.2
Can a gut scan rule out a bowel disease?
No. The scan reads how much trouble you are having; it cannot see whether this is irritable bowel syndrome, an intolerance, coeliac disease or something else. Only a doctor can rule those out, sometimes with a blood or stool test.
Sources
Every source below was checked on the day this article was published. The numbering follows the text.
- Sperber AD, Bangdiwala SI, Drossman DA, et al. Worldwide prevalence and burden of functional gastrointestinal disorders, results of Rome Foundation Global Study. Gastroenterology, 2021. doi.org/10.1053/j.gastro.2020.04.014
- Thuisarts.nl (Nederlands Huisartsen Genootschap). I have irritable bowel syndrome (PDS). thuisarts.nl
- Ballou S, Singh P, Nee J, et al. Prevalence and associated factors of bloating: results from the Rome Foundation Global Epidemiology Study. Gastroenterology, 2023. doi.org/10.1053/j.gastro.2023.05.049
- Lasser RB, Bond JH, Levitt MD. The role of intestinal gas in functional abdominal pain. New England Journal of Medicine, 1975. doi.org/10.1056/NEJM197509112931103
- Lacy BE, Mearin F, Chang L, et al. Bowel disorders. Gastroenterology, 2016. doi.org/10.1053/j.gastro.2016.02.031
- Halmos EP, Power VA, Shepherd SJ, Gibson PR, Muir JG. A diet low in FODMAPs reduces symptoms of irritable bowel syndrome. Gastroenterology, 2014. doi.org/10.1053/j.gastro.2013.09.046
- Lewis SJ, Heaton KW. Stool form scale as a useful guide to intestinal transit time. Scandinavian Journal of Gastroenterology, 1997. doi.org/10.3109/00365529709011203
- Svedlund J, Sjödin I, Dotevall G. GSRS: a clinical rating scale for gastrointestinal symptoms in patients with irritable bowel syndrome and peptic ulcer disease. Digestive Diseases and Sciences, 1988. doi.org/10.1007/BF01535722
Written by

BioProfile analyses your health status to guide you and your coach. It does not make a diagnosis, only a doctor can do that. Built on validated health questionnaires; the combined BioProfile score is not itself a validated clinical instrument yet. Your answers stay private (GDPR).